Similar Posts
FBI’s August 18 Briefing: full text
A transcript of the FBI’s scientific (afternoon of Aug. 18, 2008) briefing for media can be found here.
WA launches flu vaccine inquiry / Sydney Morning Herald
From the SMH (Good on ya, Ozzies, for taking this seriously’): The West Australian government has launched an inquiry into the flu vaccinations that caused adverse reactions in hundreds of children across the nation. WA Health Minister Kim Hames said the inquiry would scrutinise systems used to identify public health risks, including vaccine side-effects and…
Excellent comics for the new Dystopia. Check them out. You will enjoy them.
https://wrenchinthegears.com/2022/08/24/eves-fabulous-social-impact-finance-zine-please-share/
HUGE TURNAROUND: Republican National Committee goes FAR condemning NSA surveillance and seeks to hold officials accountable / Atlantic and TIME
From the Atlantic: … the GOP establishment is changing along with its elected officials; the RNC voted in a winter meeting to literally renounce NSA domestic surveillance. “It was passed by a voice vote as part of a package of RNC proposals,” Benjy Sarlin reports. “Not a single member rose to object or call for further debate,…
Disposing of chemical weapons / BBC
You can hire mobile units to destroy chemical weapons (including those in munitions) from Eisenmann Corp. near Stuttgart, Germany if the US Army won’t share its mobile units with Syria or with its own chemical weapons activities in Blue Grass, Kentucky and Pueblo, Colorado. The US stockpile could be destroyed within a year if these…
Israeli TV: Vaccine offers virtually no protection from infection; it may prevent more serious disease
In the Israeli TV news report below, the ugly truth comes out: The Vax’d can get and spread COVID to others JUST AS BADLY AS UN-VAXXED. And the reporter asks why are we not checking the vaccinated for infection when we know they are just as likely to be infected and just as likely to…
9 Comments
Comments are closed.
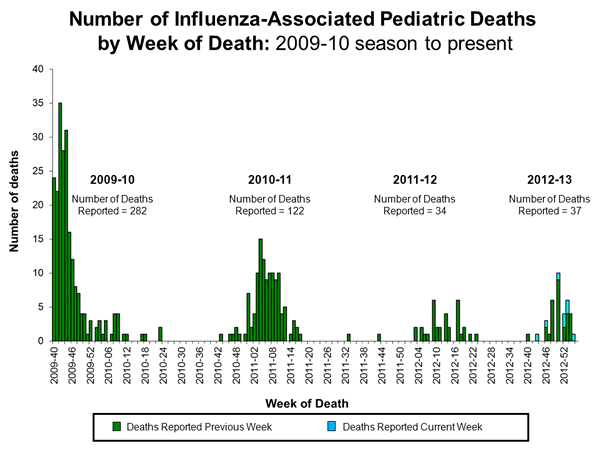
Are the turquoise bars indicative of later downward revisions (like with economic statistics)?
I guess I'm unsure why there are still turquoise bars several weeks later when the category is listed as "current week."
I'd love to know more about this as I don't remember seeing them before.
Thanks, Dr. Nass
My understanding is that the turquoise bars are upward revisions to deaths that CDC was notified about late (occurring beyond a week earlier). Still , one can see that the death toll in children is relatively low for a flu season.
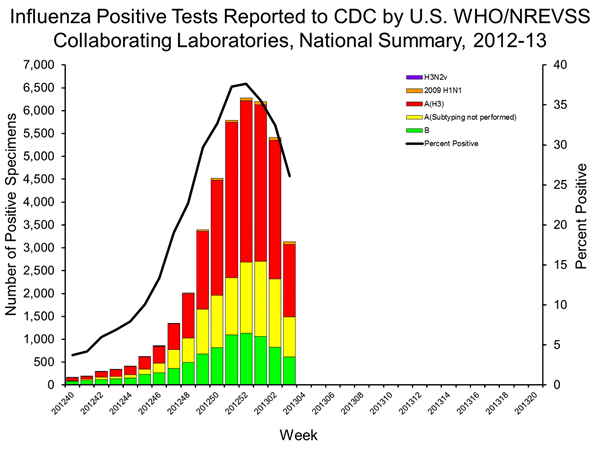
CDC is now saying that deaths in the elderly are quite high this season, but because deaths in elders are not tracked individually, as they are for children, and CDC makes guesses based on composite respiratory deaths from viral and bacterial diseases, it is difficult to know what infection(s) are contributing to higher deaths in elders.
Thanks, Dr. Nass. the CDC info your state was corroborated by our SDH Subject Matter Expert on respiratory diseases. She presented on Flu and H1N1
to our Infectious Epi class I'm in this past week (Mon)
She admitted the 36,000/year mortality statistics were based on pretty flimsy data (which I was surprised by). She was very open and honest with our class about limitations and whatnot (and I asked a lot of questions).
Here's some highlights (my notes from class) if it's interesting for you or your readers:
What constitutes an influenza death? must have flu positive test and must have died (that’s it??); don’t need to have died from flu (this will seriously overstate); now SDH is pulling death certificate deaths and going back (risk to this in overstating).
Next year we’re changing our communicable dis rule.
Before –no rule 2003 – in TX and CO huge amt of pediatric deaths in the winter; looked into it and found that flu was causing all of these
2004 – CSTE – proposed that all pediatric deaths are reportable, nationally notifiable (ISDH has to be held accountable); so they recommended
2005 – PED (pediatric) deaths nationally notifiable. Her question was what about the other people? CSTE was less concerned about elderly deaths? Richards – we have a rule on the book that should be enforceable? If you have a rule – all physicians, hospitals, and ;
2006 – 6 states hopped on board. Emergency Rule:
2013 – hardly any PED deaths; mostly elderly. IN has more data; more outbreaks in Long-term care facilities.
Phys, hosp – must report any human that dies with a positive test (including rapid-test and ANY test, other than a serology);
death would be in the county they reside.
– many times flu was diagnosed
– death certificate data (problem – usually takes 2-3 years to “approve” death statistics).
Her range for annual flu mortality btwn 3k and 36,000k
Question – how can one tell if the flu is clinical or subclinical or a consequence of other underlying medical conditions.
Ans: can’t. Data is very poor.
Send it out to county health dept to confirm
2013 – Of the 44 deaths, more than 50% were vaccinated (a little high). This makes the efficacy much less.
Tons more, and I'd be willing to send the ppt to anyone who wants info from the SDH'sNext year we’re changing our communicable dis rule.
Before –no rule 2003 – in TX and CO huge amt of pediatric deaths in the winter; looked into it and found that flu was causing all of these
2004 – CSTE – proposed that all pediatric deaths are reportable, nationally notifiable (ISDH has to be held accountable); so they recommended
2005 – PED (pediatric) deaths nationally notifiable. Her question was what about the other people? CSTE was less concerned about elderly deaths? Richards – we have a rule on the book that should be enforceable? If you have a rule – all physicians, hospitals, and ;
2006 – 6 states hopped on board. Emergency Rule:
2013 – hardly any PED deaths; mostly elderly. IN has more data; more outbreaks in Long-term care facilities.
Phys, hosp – must report any human that dies with a positive test (including rapid-test and ANY test, other than a serology); death would be in the county they reside.
– many times flu was diagnosed
– death certificate data (problem – usually takes 2-3 years to “approve” death statistics).
Her range for annual flu mortality – 3k – 36,000k –
Question – how can one tell if the flu is clinical or subclinical or a consequence of otNext year we’re changing our communicable dis rule.
Before –no rule 2003 – in TX and CO huge amt of pediNext year we’re changing our communicable dis rule.
Before –no rule 2003 – in TX and CO huge amt of pediatric deaths in the winter; looked into it and found that flu was causing all of these
Cot'd.
2004 – CSTE – proposed that all pediatric deaths are reportable, nationally notifiable (ISDH has to be held accountable); so they recommended
2005 – PED (pediatric) deaths nationally notifiable. Her question was what about the other people? CSTE was less concerned about elderly deaths? Richards – we have a rule on the book that should be enforceable? If you have a rule – all physicians, hospitals, and ;
2006 – 6 states hopped on board. Emergency Rule:
2013 – hardly any PED deaths; mostly elderly. IN has more data; more outbreaks in Long-term care facilities.
Phys, hosp – must report any human that dies with a positive test (including rapid-test and ANY test, other than a serology); death would be in the county they reside.
– many times flu was diagnosed
– death certificate data (problem – usually takes 2-3 years to “approve” death statistics).
Her range for annual flu mortality – 3k – 36,000k –
Question – how can one tell if the flu is clinical or subclinical or a consequence of other underlying medical conditions. Ans: can’t. Data is very poor.
Send it out to county health dept to confirm
2013 – Of the 44 deaths, more than 50% were vaccinated (a little high). This makes the efficacy much less.
atric deaths in the winter; looked into it and found that flu was causing all of these
2004 – CSTE – proposed that all pediatric deaths are reportable, nationally notifiable (ISDH has to be held accountable); so they recommended
2005 – PED (pediatric) deaths nationally notifiable. Her question was what about the other people? CSTE was less concerned about elderly deaths? Richards – we have a rule on the book that should be enforceable? If you have a rule – all physicians, hospitals, and ;
2006 – 6 states hopped on board. Emergency Rule:
2013 – hardly any PED deaths; mostly elderly. IN has more data; more outbreaks in Long-term care facilities.
Phys, hosp – must report any human that dies with a positive test (including rapid-test and ANY test, other than a serology); death would be in the county they reside.
– many times flu was diagnosed
– death certificate data (problem – usually takes 2-3 years to “approve” death statistics).
Her range for annual flu mortality – 3k – 36,000k –
Question – how can one tell if the flu is clinical or subclinical or a consequence of other underlying medical conditions. Ans: can’t. Data is very poor.
Send it out to county health dept to confirm
2013 – Of the 44 deaths, more than 50% were vaccinated (a little high). This makes the efficacy much less.
her underlying medical conditions. Ans: can’t. Data is very poor.
Send it out to county health dept to confirm
2013 – Of the 44 deaths, more than 50% were vaccinated (a little high). This makes the efficacy much less.
mouth on what current and future policies and rules are looking like, as well as some of the science.
Enjoy.
Thanks for this discussion.
I think this issue of the number of flu deaths in children and adults is very important. Pediatric deaths are rarely missed: they are required to be sent to state health departments, and investigated if they occur at home. So the case numbers should be pretty good.
Yet CDC multiplied the reported pediatric deaths in 2009-10 to create an estimate of deaths. This multiplication will overestimate cases.
In adults, we simply do not know what the flu death rate is, we cannot calculate benefit and we collect almost no data on flu vaccine adverse events. So no risk-benefit analysis can be performed.
According to longstanding public health principles, you only create a public health program (like flu vaccination recommendations for everyone over 6 months in the US) if there is a large benefit compared to risk and cost. Yet that has never been done in the US…and almost no other countries recommend flu vaccine for more than high risk groups.
Somehow those previous messages got all jumbled up. Strange, I did a simple copy and paste to make one message into two. Sorry about that.
Do you remember the multiplication factor they used in 2009-10 and how they justified that number?
Thanks so much for sharing your perspective on here. I've been learning from you now for some 3-4 years. I can ask you questions that I can only ask very infrequently in class and with a lot of diplomacy, because of the religion surrounding these things.
Here is a discussion on CDC's website about it estimates. My reading of this indicates they are cagey about providing a model or algorithm for the estimates they make, instead claiming to review various types of figures and then creating an estimate…but how exactly this is done is not shared.
I do not believe they provided a multiplication factor for the pedi deaths, but since all pedi deaths must be reported, why should there be any factor applied to this total to get a larger estimate?
Here is the URL:
http://www.cdc.gov/flu/about/disease/us_flu-related_deaths.htm